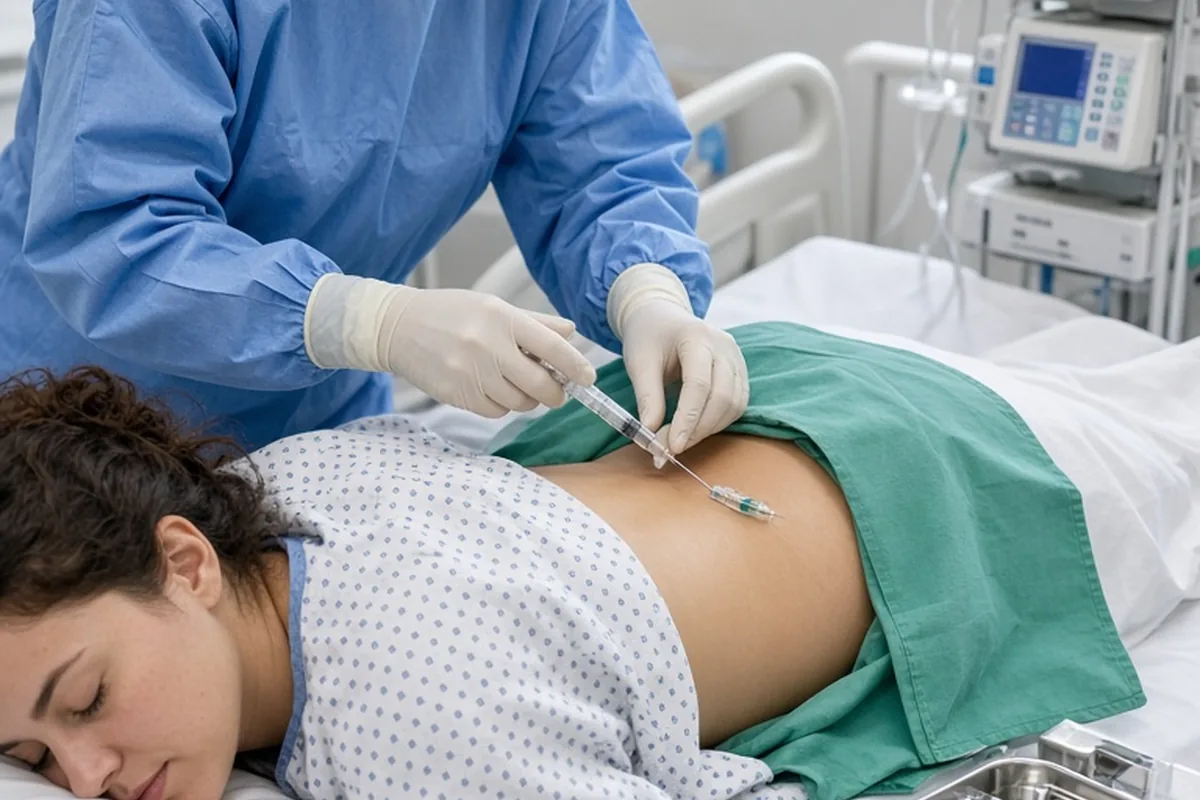
An epidural typically costs between one thousand and four thousand dollars without insurance, depending on the hospital, geographic region, and the duration of labor. Insured patients usually pay significantly less out of pocket, often between two hundred and one thousand five hundred dollars through copayments, coinsurance, and deductibles, provided that both the attending anesthesiologist and the birthing facility participate in the patient network.
Preparing for the financial side of childbirth can feel overwhelming, especially when medical procedures involve separate provider bills and unpredictable labor timelines. Understanding how labor analgesia is priced helps families anticipate out-of-pocket expenses and make confident healthcare choices.
Understanding the Components of Epidural Billing
A standard medical bill for an epidural rarely appears as a single line item. Instead, hospital billing systems separate the physical placement of the catheter, the continuous administration of medication, and the specialized clinical monitoring required throughout labor. The primary charge comes from the professional fee billed directly by the anesthesiologist or certified registered nurse anesthetist who performs the procedure. This fee reflects their clinical expertise, the sterile placement between spinal vertebrae, and ongoing management until delivery.
In addition to the clinician fee, the hospital charges a facility fee that covers the physical equipment and pharmaceuticals. This includes the epidural insertion tray, sterile drapes, local anesthetics such as bupivacaine, opioid adjuncts like fentanyl, infusion pumps, and emergency resuscitation supplies kept on standby. Because facilities calculate equipment and medication charges separately from professional services, parents often receive two distinct bills for the same procedure weeks after returning home.
Understanding this split billing structure is crucial for accurate financial planning. If you only obtain an estimate for the hospital facility charge, you might be caught off guard when an independent anesthesia group sends an additional bill. Clarifying whether a written quote encompasses both professional and facility fees ensures you evaluate the complete price before delivery day.
- Professional fee: Covers the anesthesiologist or nurse anesthetist for placement and continuous monitoring.
- Facility fee: Accounts for sterile catheter kits, specialized infusion tubing, and emergency supplies.
- Pharmacy charges: Covers the specific local anesthetic and analgesic drug formulations used throughout labor.
Average Out-of-Pocket Expenses With Health Insurance
When you have commercial health insurance, the amount you pay for an epidural depends heavily on your plan deductible, coinsurance rate, and out-of-pocket maximum. Most major health plans categorize epidural analgesia as a standard component of maternity care rather than an elective procedure. However, because labor and delivery often consume a substantial portion of an annual deductible, the epidural itself may be subject to coinsurance charges ranging from ten to thirty percent of the negotiated rate.
For an insured patient delivering at an in-network facility, out-of-pocket epidural costs generally fall between two hundred and one thousand five hundred dollars. If your delivery occurs early in the plan year before you have met your annual deductible, your initial financial responsibility will be higher. Conversely, if previous prenatal visits, ultrasounds, or diagnostic screenings have already met your deductible, your expense for the epidural may consist solely of your plan coinsurance or a modest flat copayment.
A key variable in insured billing involves out-of-pocket limits. Most family plans establish a maximum cap on annual medical spending. If the total cost of hospital admission, physician fees, and newborn nursery care reaches this ceiling, your insurance policy covers remaining covered expenses at one hundred percent, effectively reducing the incremental cost of the epidural to zero.
Self-Pay and Uninsured Epidural Price Ranges
Patients without health insurance or those choosing to pay directly outside their coverage network face gross chargemaster rates that frequently range from two thousand to upwards of four thousand five hundred dollars for an epidural alone. These baseline retail numbers reflect standard hospital list prices before any contractual discounts are applied. When combined with overall hospital delivery charges, total birth expenses can escalate rapidly without clear upfront agreements.
Fortunately, almost all hospitals maintain dedicated self-pay discount policies for uninsured patients. When requested in advance, billing offices routinely apply prompt-pay discounts that reduce gross fees by thirty to sixty percent. For example, a three thousand dollar anesthesia bill might be adjusted down to one thousand two hundred dollars if paid in full before discharge or arranged on an agreed monthly schedule.
To access these adjusted rates, self-pay patients should contact the financial counseling department of their intended hospital well before the third trimester. Requesting an itemized, bundled self-pay maternity package often produces substantial savings compared to accepting individual post-delivery invoices. Ensure you obtain the agreement in writing to prevent downstream disputes with independent anesthesia practices.
Key Factors That Influence Total Analgesia Costs
The overall cost of labor analgesia is not uniform across hospitals or individual patients. One of the most significant variables is the total duration of the epidural infusion. Many anesthesia groups bill using a base unit value for the insertion combined with time units calculated in fifteen-minute increments. A rapid four-hour labor will generate fewer billable monitoring units than an extended twenty-four-hour induction, resulting in noticeable price differences even within the same hospital wing.
Geographic location also plays a dominant role in healthcare pricing. Metropolitan areas with higher operating overhead, regional labor rates, and medical malpractice premiums consistently charge more for obstetrical anesthesia than rural community hospitals. A hospital in a high-cost urban center may bill double the amount for the same standardized catheter placement compared to a regional facility a few hours away.
Clinical complexity represents another critical pricing factor. If a patient experiences anatomical challenges, severe scoliosis, or previous spinal surgery requiring extended ultrasound-guided placement, additional procedural codes may be applied. Similarly, if a laboring mother transitions to an unplanned emergency cesarean section, the anesthesiologist must administer higher-potency surgical anesthesia, modifying the final billing code.
Preventing Out-of-Network Anesthesia Surprises
A historical challenge in maternity billing occurred when an expectant mother selected an in-network hospital and obstetrician, only to have an on-call anesthesiologist who was out-of-network administer pain relief. Under previous billing practices, this resulted in surprise balance billing where the patient was held liable for thousands of dollars in uncovered charges. Federal legislation, such as the No Surprises Act, now offers protection against most unexpected out-of-network balance bills for emergency and non-elective hospital services.
Under these protections, if you deliver at an in-network facility, out-of-network anesthesiologists generally cannot charge you more than your plan in-network cost-sharing amount. The insurer and the anesthesia provider must negotiate the balance directly or enter independent dispute resolution without transferring the financial burden to the patient. This statutory safeguard provides essential financial peace of mind during labor.
Even with legal protections in place, administrative errors can still occur on initial billing statements. It remains wise practice to verify in advance whether the hospital contracted anesthesia group participates with your insurance network. If you receive an out-of-network bill showing full charges, immediately contact both your insurer and the hospital billing department to request a review under federal surprise billing guidelines.
Questions to Ask Your Hospital and Insurer Before Delivery
Proactive communication is the most reliable defense against unexpected maternity bills. Around the twentieth to twenty-eighth week of pregnancy, contact your health insurance member services department with specific procedure codes. Ask them for your remaining deductible balance, your coinsurance percentage for inpatient anesthesia, and whether your plan requires pre-authorization for labor pain management services.
Next, speak directly with the financial clearance or billing office at your planned birth center or hospital. Ask for the specific tax identification number of the facility as well as the name of the independent anesthesia group providing coverage for labor and delivery. Confirming that both entities are contracted with your exact plan tier prevents miscommunications that can arise when a hospital is in-network but individual clinical groups are not.
Consider asking the hospital billing office for an itemized estimate using their public pricing transparency tools or an online patient portal calculator. While these estimates are subject to the unpredictable nature of labor, having a documented projection establishes a reliable baseline against which you can compare your final explanation of benefits and medical invoices.
- What is my remaining deductible, and what coinsurance applies to inpatient anesthesia services?
- Does the independent anesthesia group contracted by the hospital participate in my insurance network?
- Are there separate facility charges for continuous epidural infusion pumps and pharmacy supplies?
- What is the standard prompt-pay discount if any portion of the bill is paid out of pocket?
Managing and Negotiating Postpartum Medical Bills
When the delivery bills arrive, refrain from paying them immediately without thorough review. The first document you receive from your insurance company should be an Explanation of Benefits (EOB), not a direct invoice. Compare the EOB carefully against the subsequent billing statements sent by the hospital and anesthesia practice to ensure that dates of service, procedure codes, and patient responsibility amounts match exactly.
If you identify discrepancies or charges that exceed your expectations, request an itemized statement detailing every fee code, medication charge, and monitoring interval. Billing errors, such as duplicate entry of sterile trays or misapplied deductible calculations, occur frequently in high-volume hospital departments. Pointing out these administrative inconsistencies often leads to immediate downward adjustments.
When facing a valid balance that strains your household budget, ask the provider billing department about interest-free installment plans or hardship discounts. Most medical networks offer twelve-to-thirty-six-month repayment schedules without penalties, and many will extend a ten to twenty percent discount if you offer to settle the remaining balance in a single lump sum.
Frequently asked questions
Can I get an epidural if I cannot afford to pay upfront?
Yes, hospitals in the United States cannot deny medically necessary labor pain management due to an inability to pay upfront. Under federal emergency care regulations, clinical teams evaluate and treat laboring patients regardless of their immediate financial or insurance status. Billing discussions and payment arrangements take place after delivery.
Does Medicaid cover the complete cost of an epidural?
In virtually all states, Medicaid maternity coverage pays for labor and delivery services in full, including medically indicated epidural analgesia. When you deliver at a participating Medicaid facility, covered pain management entails zero out-of-pocket copayments or coinsurance costs for the patient.
Why did I receive two separate bills for my epidural?
Separate bills occur because hospitals and anesthesia providers bill independently under standard medical billing systems. One statement covers the facility equipment, medication, and disposable supplies, while the second bill covers the professional services and continuous monitoring performed by the anesthesiologist.
Is an epidural more expensive than alternative pain relief options?
Yes, an epidural is generally more expensive than nitrous oxide or intravenous narcotics because it requires specialized catheter placement and dedicated clinical monitoring. While systemic medications carry lower procedural costs, many parents find the comprehensive pain relief of an epidural well worth the added expense.
Your next step
Call your birthing hospital and insurance provider today to verify in-network anesthesia coverage and obtain a written estimate for your labor pain relief plan.