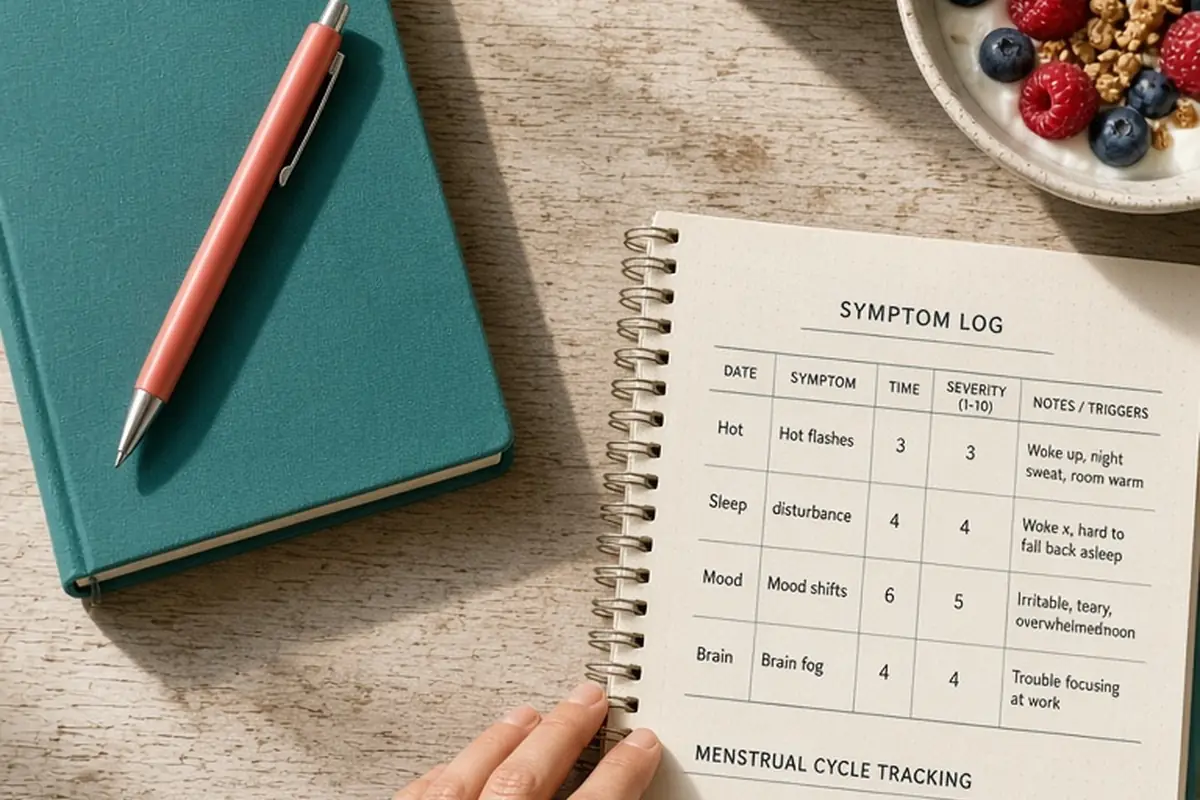
A menopause appointment checklist helps you organize symptom timelines, menstrual changes, medical history, and daily functional impacts before meeting with your clinician. By bringing a written log of hot flashes, sleep disturbances, mood shifts, current medications, and prioritized treatment goals, you ensure your provider can accurately assess your stage of perimenopause or postmenopause and develop a safe, tailored management plan.
Navigating the transition through perimenopause and menopause involves complex physical and emotional changes driven by shifting ovarian hormone production. Because appointment times are often limited, arriving with a structured record of your symptoms, personal health background, and specific treatment preferences allows your healthcare provider to evaluate your needs thoroughly and recommend evidence-based care.
Documenting Your Symptom Frequency, Severity, and Daily Impact
The first step in preparing for a menopause consultation is creating a concrete, dated record of your physical and emotional symptoms over several weeks or months. Vasomotor symptoms, such as hot flashes and night sweats, vary widely in intensity and duration. Note how many episodes you experience during the day, how often night sweats wake you from sleep, and whether specific factors like caffeine, warm environments, or stress seem to trigger them. Alongside vasomotor events, record cognitive and mood changes, including brain fog, memory lapses, irritability, and uncharacteristic anxiety. Having specific counts and descriptions prevents symptoms from being minimized or overlooked during a short consultation.
Equally important is logging genitourinary symptoms and changes in physical comfort. Vaginal dryness, pain during intercourse, urinary urgency, and frequent urinary tract infections are common markers of the genitourinary syndrome of menopause, yet many patients feel hesitant to bring them up without prompting. Document any sleep architecture disruptions, joint stiffness, palpitations, or skin and hair changes. Quantifying how these symptoms affect your work productivity, emotional well-being, and relationships gives your clinician a clear picture of how significantly hormonal fluctuations are altering your quality of life.
- Log the daily frequency, duration, and severity of hot flashes and night sweats.
- Track sleep interruptions and whether awakenings are caused by temperature spikes or primary insomnia.
- Note any pain, dryness, irritation, or urinary changes with dates and attempted over-the-counter remedies.
- Record mood fluctuations, cognitive fatigue, and their specific impact on daily routines.
Further reading: Office on Women's Health
Tracking Menstrual Cycle Changes and Contraceptive Status
During perimenopause, ovarian hormone output fluctuates unpredictably, leading to irregular menstrual patterns that can persist for several years before complete cessation. Record the start dates, duration, and flow characteristics of your recent periods. Note whether your cycles have shortened, lengthened, skipped entirely, or presented with unusually heavy bleeding or mid-cycle spotting. Sudden changes in bleeding volume, such as soaking through protection within an hour or passing large clots, represent vital clinical data that helps your provider distinguish normal transition patterns from uterine polyps, fibroids, or endometrial abnormalities.
Clarifying your contraceptive status is an essential part of this discussion. Fertility declines significantly during perimenopause, but spontaneous ovulation can still occur until a woman reaches clinical menopause, defined as twelve consecutive months without a menstrual period. Reviewing your current birth control method helps your clinician evaluate whether your symptoms might be masked by hormonal contraceptives or if a different contraceptive option would better manage both cycle irregularity and pregnancy prevention. Method selection depends on your medical history, cardiovascular risk factors, and personal preferences as guided by clinical protocols.
- Document cycle start dates, interval lengths, and flow intensity over the past six to twelve months.
- Highlight abnormal bleeding patterns, including post-coital bleeding or spotting between periods.
- List all current and past contraceptive methods used, including hormonal, barrier, or permanent options.
Further reading: CDC: Contraception and birth control methods
Further reading: Office on Women's Health
Compiling Personal Medical History, Family Records, and Medications
A thorough health history determines which management options are safest and most effective for your body. Gather your personal medical records, noting chronic conditions such as hypertension, diabetes, migraines, thyroid disorders, autoimmune diseases, or gallbladder problems. List your surgical history, specifically detailing any gynecological procedures such as uterine ablation, ovarian surgery, or hysterectomy, noting whether your ovaries were retained or removed. This surgical context directly determines whether systemic estrogen therapy requires an accompanying progestogen to protect the uterine lining.
Family medical history provides critical context for assessing long-term health risks that accelerate after menopause, particularly cardiovascular disease, osteoporosis, and hormone-sensitive cancers. Note whether first-degree relatives had breast, ovarian, uterine, or colorectal cancer, as well as any family history of blood clots, strokes, or early heart attacks. Additionally, compile an exhaustive list of all prescription medications, over-the-counter drugs, botanicals, and dietary supplements you consume, including dosages and frequencies. Many herbal remedies marketed for menopause can interact with prescription therapies or influence liver enzyme pathways, making full disclosure vital.
- List all diagnosed chronic conditions, previous surgeries, and dates of relevant procedures.
- Detail first-degree family history regarding cardiovascular events, bone fractures, and malignancies.
- Bring an up-to-date medication list specifying brand or generic names, doses, and supplement ingredients.
Further reading: Office on Women's Health
Clarifying Goals Across Hormonal, Non-Hormonal, and Lifestyle Options
Entering your appointment with defined treatment priorities allows you to guide the conversation toward solutions that match your health values. Consider what outcome matters most to you right now: is it eliminating debilitating night sweats to restore sleep, resolving painful intercourse, stabilizing mood swings, or protecting long-term bone density? Knowing your primary goal prevents the visit from becoming overwhelming when reviewing multiple therapeutic avenues, allowing you and your clinician to address the most distressing symptoms first.
Familiarize yourself with the broad categories of available interventions so you can participate in shared decision-making. Systemic hormone therapy, delivered via transdermal patches, gels, sprays, or oral formulations, provides robust relief for vasomotor symptoms and helps prevent bone loss, but requires clinical evaluation of individual risk factors. Localized vaginal estrogen therapies address genitourinary symptoms with minimal systemic absorption. For individuals who have contraindications to hormones or prefer not to use them, non-hormonal prescription medications and targeted lifestyle adjustments involving nutrition, resistance exercise, and temperature management offer viable alternatives.
- Identify your top two or three health goals for immediate symptomatic relief and preventive wellness.
- Determine your openness to systemic hormone therapy, local vaginal therapies, or non-hormonal medications.
- Discuss realistic lifestyle adjustments, such as strength training, dietary changes, and stress reduction techniques.
Further reading: Office on Women's Health
Prioritizing Questions for Your Clinician During the Menopause Consultation
Because clinical appointments often pass quickly, write down your questions beforehand and rank them in order of importance. Begin the conversation by stating your primary concerns immediately rather than waiting until the end of the visit. You might ask whether your symptom cluster aligns with perimenopause, what diagnostic tests or screening evaluations are appropriate for your age, and how your current cardiovascular and metabolic markers influence your treatment options. Asking clear questions helps keep the discussion focused on clinical evidence rather than vague reassurance.
Inquire about the risks, benefits, and expected timelines for any recommended interventions. Ask how long a medication typically takes to show noticeable improvement, what common side effects might emerge during the initial weeks, and when a follow-up visit should be scheduled to reassess your progress. If local vaginal therapy or non-hormonal options are proposed, confirm how long therapy should continue and whether dosage modifications might be necessary over time. Clear communication during the visit ensures you leave with an actionable, realistic plan.
- Ask: Based on my symptom log and history, am I in perimenopause or postmenopause?
- Ask: Which treatment options best balance symptom relief with my personal health risk factors?
- Ask: What routine preventive screenings, such as mammograms, lipid panels, or bone density scans, do I need?
- Ask: How soon should I expect symptom improvement, and what side effects warrant a call to the clinic?
Further reading: Office on Women's Health
Navigating Insurance Coverage, Diagnostic Tests, and Specialist Referrals
Understanding how your insurance plan handles menopause-related care prevents unexpected medical expenses. Hormone blood tests, such as follicle-stimulating hormone or estradiol levels, fluctuate widely during perimenopause and are rarely necessary for clinical diagnosis in women over age forty-five experiencing classic symptoms. However, your clinician may recommend baseline blood work to rule out other conditions that mimic menopausal symptoms, such as thyroid dysfunction, iron deficiency anemia, or vitamin deficiencies. Contact your insurer or check your plan documents to understand copays and coverage criteria for diagnostic blood panels and preventive imaging.
If your primary care provider or gynecologist does not have specialized training in midlife women's health or dismisses your concerns, request a referral to a certified menopause specialist. Many clinicians have completed advanced credentialing in menopause management and stay current on evolving hormone formulations, non-hormonal alternatives, and individualized risk stratification. Advocating for a second opinion or a specialized consultation ensures you receive care grounded in contemporary guidelines rather than outdated assumptions.
- Check insurance coverage policies and network status for specialist consultations and preventive screenings.
- Clarify which diagnostic lab tests are medically necessary versus optional.
- Seek a referral to an accredited menopause practitioner if your current provider lacks midlife health expertise.
Further reading: Office on Women's Health
Developing an Ongoing Monitoring and Follow-Up Strategy
Managing menopause is an ongoing process rather than a single clinical encounter. After initiating or adjusting any therapeutic regimen, maintain a simplified daily or weekly symptom tracker to record changes in hot flash frequency, sleep quality, bleeding patterns, or localized comfort. Most hormonal and non-hormonal therapies require four to twelve weeks of consistent use before full therapeutic benefits are realized. Tracking your trajectory gives your provider concrete data during your follow-up appointment to determine whether to maintain, adjust, or switch your regimen.
Establish clear boundaries regarding when to contact the clinic between scheduled appointments. While mild breast tenderness, transient nausea, or minor spotting can occur when starting hormone therapy, unexpected heavy vaginal bleeding after menopause, new severe headaches, chest discomfort, or sudden unilateral leg swelling require prompt medical evaluation. Having a direct communication pathway through your provider's patient portal ensures that minor concerns are addressed promptly while potential safety signals receive rapid clinical attention.
- Schedule a follow-up appointment for eight to twelve weeks after starting any new therapy.
- Continue logging symptom intensity and any new side effects to evaluate treatment efficacy.
- Review red-flag symptoms with your doctor that require immediate medical attention.
Further reading: Office on Women's Health
Frequently asked questions
Do I need hormone blood tests to confirm that I am in perimenopause or menopause?
For most women over age 45 experiencing irregular cycles and classic vasomotor symptoms, hormone blood tests are not required for diagnosis because estrogen and follicle-stimulating hormone levels fluctuate unpredictably day to day. Clinicians typically diagnose perimenopause and menopause based on age, symptom history, and menstrual changes. Blood tests are primarily utilized when symptoms occur before age 40 or to evaluate alternative conditions such as thyroid disorders.
Can I still get pregnant if I am experiencing perimenopausal symptoms?
Yes, pregnancy remains possible throughout perimenopause because ovulation can still occur unpredictably even when menstrual cycles are irregular. Clinical guidance recommends continuing reliable contraception until you have gone twelve consecutive months without a period if you are over age 50, or twenty-four months if you are under age 50. Discuss suitable birth control options with your provider that align with your cardiovascular and overall health profile.
How should I prepare if my appointment is scheduled as a telehealth visit?
Prepare for a telehealth menopause visit by logging your recent symptoms, menstrual dates, and questions on paper or in a document beside your screen. Take your blood pressure and current weight before the call if you have home monitoring devices, and have all medication and supplement bottles within reach. Ensure you are in a quiet, private space where you can speak candidly about sensitive physical, emotional, and sexual health symptoms.
What should I do if my doctor dismisses my menopause symptoms as normal aging?
If a healthcare provider dismisses your symptoms without offering evaluation or evidence-based management options, remember that you have the right to seek comprehensive midlife care. Ask for your records, document the specific functional impairments you are experiencing, and schedule a consultation with a clinician certified in menopause management. Specialized providers are trained to evaluate the risks and benefits of modern therapeutic options tailored to your specific needs.
Your next step
Print or write down your detailed symptom log, complete medication list, and top three prioritized questions today so they are ready for your next healthcare appointment.